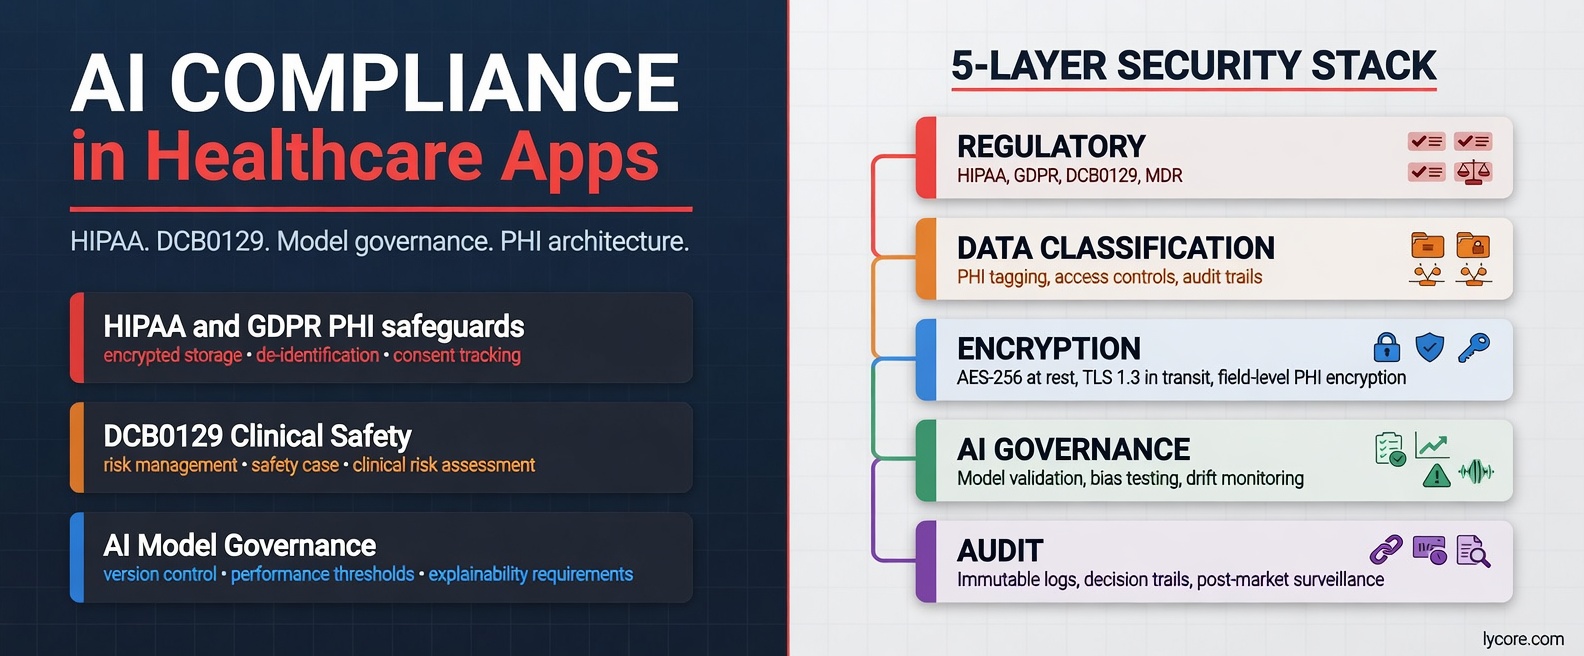
Healthcare applications operate under some of the most demanding compliance requirements of any software category. HIPAA and state health privacy laws, FDA oversight of software that functions as a medical device, ONC certification rules for health IT, and GDPR for any patients in Europe create a compliance landscape that is both technically and procedurally complex. AI compliance in healthcare adds another dimension: AI systems that make or assist clinical decisions face additional regulatory scrutiny, and the consequences of compliance failures — data breaches, incorrect clinical outputs, regulatory sanctions — are measured in patient harm, not just financial penalties. This guide covers the compliance and risk architecture that healthcare applications require in 2026, with specific attention to where AI capabilities change the regulatory calculus.
The Healthcare Compliance Landscape for AI Applications
Healthcare AI applications face overlapping regulatory frameworks that must be addressed simultaneously:
- Data protection regulation: the HIPAA Privacy, Security, and Breach Notification Rules, the FTC Health Breach Notification Rule for consumer health apps outside HIPAA, state laws such as Washington’s My Health My Data Act, and EU GDPR for European patients, governing how personal health data is collected, stored, processed, and shared
- Medical device regulation: FDA Software as a Medical Device (SaMD) policy, the FDA clinical decision support (CDS) software guidance (revised January 2026), and FDA guidance on predetermined change control plans for AI-enabled device software, plus EU MDR for products sold in Europe; applies when AI output influences clinical decisions
- Clinical governance and certification: ONC Health IT Certification Program requirements for decision support interventions in certified EHRs, The Joint Commission standards for accredited care organizations, and CMS Conditions of Participation, governing the safety and transparency of software used in care settings
- Cybersecurity frameworks: the HIPAA Security Rule, NIST CSF, HITRUST, SOC 2, ISO 27001, and FDA premarket cybersecurity requirements for connected devices, governing the security posture of systems holding health data
The critical question for any AI feature in a healthcare application: does this AI output influence a clinical decision? If yes, FDA device regulation may apply unless the function meets all four of FDA’s non-device CDS criteria, which can mean clinical validation, a 510(k), De Novo, or PMA submission, and postmarket surveillance that add 6 to 24 months to the development timeline. If no (the AI is used for administrative, operational, or non-clinical purposes), standard healthcare data protection compliance applies.
AI Compliance in Healthcare: Data Architecture Requirements
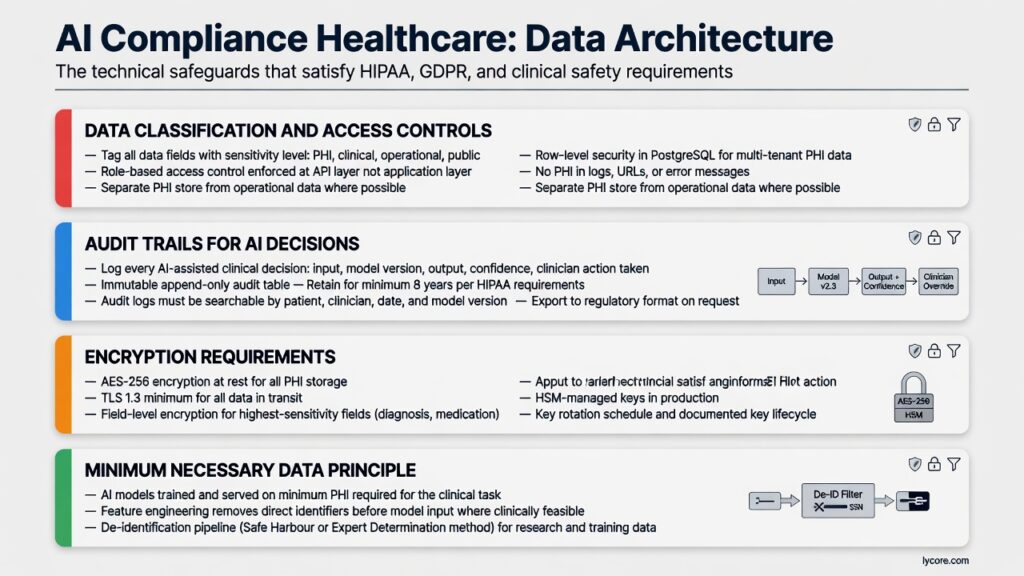
Data Classification and Access Controls
Healthcare data in an AI system requires classification at the field level: personally identifiable information (name, date of birth, Social Security number, medical record or insurance member number), protected health information (PHI — diagnoses, medications, treatment history, clinical notes), and de-identified data (clinical data de-identified under the HIPAA Safe Harbor or Expert Determination method, still subject to re-identification risk assessment). AI systems that process PHI must implement access controls at the data level — not just at the application level — using database row-level security, field-level encryption for the most sensitive data, and attribute-based access control that reflects clinical roles and relationships.
Audit Trails for AI-Assisted Decisions
AI compliance in healthcare requires complete audit trails for every AI-assisted decision: what data was the AI system given, what output did it produce, which version of the model produced it, who acted on the output, and what the outcome was. This audit trail must be immutable (cannot be altered after creation), tamper-evident (any modification is detectable), and retained for the full retention period required by applicable regulations (HIPAA requires compliance documentation to be kept for six years, while medical record retention periods are set by state law and often run longer, especially for minors). For AI systems specifically, the audit trail must also capture model version — regulatory review of adverse events requires the ability to determine exactly which model version was active when a specific decision was made.
Clinical Safety: FDA SaMD, CDS Criteria, and Safety Cases
In the US, the first clinical safety question is regulatory: is the AI feature a medical device? FDA’s clinical decision support guidance, revised in January 2026, keeps four criteria for non-device CDS: the software does not acquire or analyze medical images or signals, it displays or analyzes medical information, it supports a healthcare professional’s recommendations on prevention, diagnosis, or treatment, and it lets that professional independently review the basis for the recommendation rather than rely on it primarily. AI that analyzes images or signals, supports time-critical decisions, or hides its reasoning is likely a device function and needs an FDA pathway (510(k), De Novo, or PMA), quality system controls, and, for models that will be updated after clearance, a predetermined change control plan. Whether or not FDA clearance is needed, build a written safety case: a structured argument supported by evidence that the software is acceptably safe for its intended use. For AI systems, the safety case must address: the scope of clinical decisions the AI is intended to assist, the validation evidence supporting the AI’s output quality in the intended use context, the failure modes that could lead to patient harm, the mitigations for those failure modes, and the post-deployment monitoring approach for detecting safety signals. If the feature runs inside certified EHR software, ONC’s decision support intervention requirements also call for source attribute transparency for predictive models; confirm the current version of those rules, since ONC has proposed revisions.
This is not a checkbox exercise. A credible safety case requires clinical input (a licensed clinician who owns clinical risk sign-off), systematic hazard analysis following ISO 14971 risk management practice, and documented evidence from validation testing. Expect 3 to 6 months for a thorough safety case for a meaningful AI clinical feature, assuming the underlying validation data exists, and longer if an FDA submission is required.
HIPAA Technical Safeguards for AI Healthcare Applications
Encryption Requirements
PHI must be encrypted at rest (AES-256 minimum) and in transit (TLS 1.2 minimum, TLS 1.3 recommended). For AI systems that process PHI, this extends to the AI inference pipeline: data sent to external AI APIs (OpenAI, Anthropic, Google) must be evaluated for HIPAA Business Associate Agreement (BAA) coverage — some providers offer BAAs for healthcare customers, others do not, and sending PHI to a provider without a BAA is a HIPAA violation regardless of the technical security of the transmission. For healthcare AI applications in production, using models deployed within your own infrastructure (or a cloud provider under BAA) is often preferable to external API calls, precisely because it eliminates this regulatory exposure.
Minimum Necessary Data Principle
HIPAA’s minimum necessary standard, echoed by data minimization rules in state privacy laws and GDPR, requires that AI systems access only the minimum data necessary for the specific AI function. An AI system that summarizes clinical notes for administrative review should not have access to medication administration records. An AI triage tool should not see billing data. Implementing minimum necessary access in AI systems requires careful data access design: the AI inference pipeline receives exactly the data fields required for its specific function, not a broad export of the patient record, even if such a broad export would be technically convenient.
AI Model Governance in Healthcare
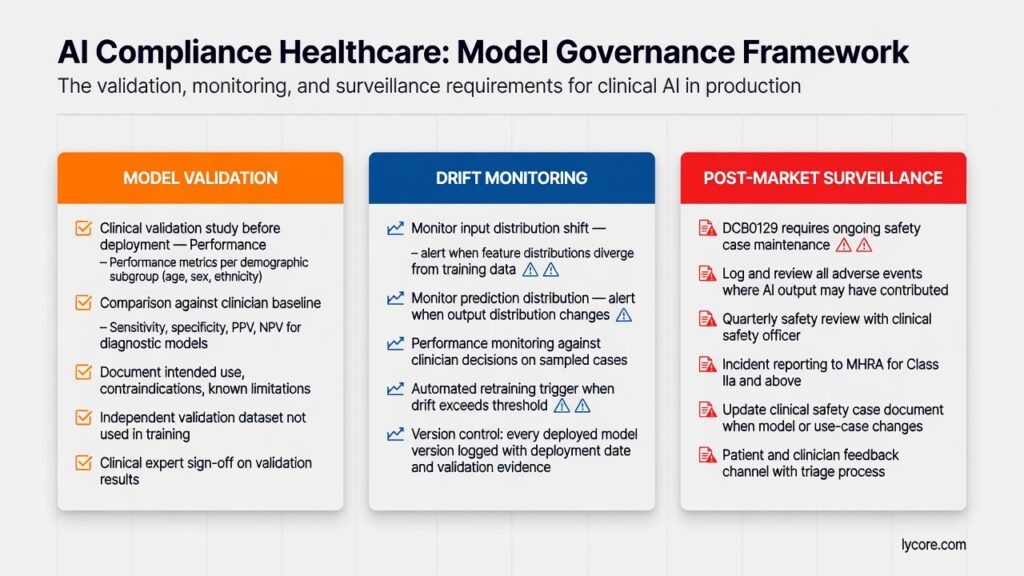
Model Validation and Population Bias
AI models trained on historical healthcare data reflect the biases present in that data: demographic biases in diagnosis rates, access-to-care biases that correlate socioeconomic factors with health outcomes, and provider biases in clinical documentation. For AI compliance in healthcare, model validation must include performance analysis disaggregated by demographic group to identify differential performance. A model that performs well on average but significantly underperforms for a specific demographic group may cause systematic harm to that group — and constitutes a regulatory and ethical risk regardless of average performance metrics. The HHS Section 1557 nondiscrimination rule also requires covered health programs to make reasonable efforts to identify and mitigate discrimination risks from patient care decision support tools, including AI, so disaggregated validation is a compliance record as well as good practice.
Model Drift Monitoring
Healthcare AI models are validated against a specific patient population at a specific point in time. As the patient population changes, as clinical practice evolves, or as the conditions that drove model training change (e.g., post-pandemic shifts in disease presentation), model performance may drift. Production healthcare AI systems require continuous performance monitoring against ground truth outcomes, with defined thresholds that trigger model review and potential revalidation when performance falls below acceptable levels.
Practical Compliance Architecture for Healthcare AI Teams
- Engage a clinical safety lead early: Not after you have built the AI feature, but before you start designing it. A licensed clinician who owns clinical risk shapes the validation requirements and the safety case approach, which in turn shapes what the AI system needs to capture and log.
- Assess medical device classification at the feature level: Each AI feature should be individually assessed against FDA’s device definition and the four non-device CDS criteria. A feature that assists administrative scheduling is not a medical device. A feature that suggests differential diagnoses may be. Get clarity before building.
- Build audit trail infrastructure as a first-class concern: Not as a retrofit. Every AI inference call, every model version deployed, every user action on an AI-generated output must be captured in an immutable audit store from day one of production operation.
- Use healthcare-specific BAA-covered AI infrastructure: For any AI capability processing PHI, use providers with signed BAAs and confirm the specific services covered. AWS, Azure, and Google Cloud all offer healthcare-focused configurations; OpenAI and Anthropic offer BAAs for enterprise healthcare customers.
- Plan for incident response: When an AI system contributes to an adverse patient outcome, there will be a regulatory review. The ability to reconstruct exactly what the AI system showed, which model version produced it, and what data it was given is not optional for this review.
For teams building broader compliance automation beyond the healthcare context, our post on AI-Driven Compliance Monitoring: Reducing Risk in Regulated Industries covers the surveillance and alerting architecture that applies across regulated industries.
Frequently Asked Questions
Does every AI feature in a healthcare app require medical device approval?
No — the threshold is whether the AI output influences a clinical decision. Administrative AI (appointment scheduling, billing code suggestion, documentation summarization for administrative purposes) typically does not meet the medical device threshold. Diagnostic AI (symptom assessment, imaging analysis, clinical decision support) typically does. In the US, FDA’s CDS criteria and digital health policies draw the line, and it is not always clear, especially for time-critical or opaque outputs. Get formal regulatory advice for any feature where the classification is ambiguous.
Can we use general-purpose LLMs (such as GPT-5 or Claude) for clinical AI features?
For non-clinical features (documentation summarization, appointment management, patient communication), yes — with appropriate BAA coverage and PHI minimization. For clinical decision support, general-purpose LLMs require extensive validation against clinical ground truth in your specific use case before deployment. They are not validated for clinical use out of the box, and their performance on clinical tasks varies significantly by clinical domain and patient population.
How long does clinical safety and FDA readiness take for a new AI feature?
For a meaningful AI clinical feature with a well-scoped clinical function, a thorough safety case and validation package takes 3 to 6 months from initiation to sign-off, assuming a clinical safety lead is engaged, the validation data exists, and the hazard analysis is conducted systematically. If the feature is a device function that needs FDA clearance, add submission preparation and FDA review time on top; FDA’s Q-Submission program lets you get feedback on the regulatory pathway before you file. Features with broader clinical scope, less validation evidence, or complex failure mode profiles take longer. Budget for this timeline before committing to a launch date.
Conclusion
AI compliance in healthcare is genuinely complex — more so than in most other regulated industries — because the consequences of getting it wrong are measured in patient harm and because the regulatory requirements are legitimately demanding. The teams that navigate this well are those who engage regulatory and clinical expertise early, build compliance infrastructure (audit trails, access controls, model governance) as first-class concerns rather than retrofits, and treat patient safety as the design constraint it actually is rather than a compliance checkbox. The AI capability investments that are genuinely valuable in healthcare will survive this scrutiny; those that aren’t won’t — and that outcome is appropriate.
If you are building AI capabilities for a healthcare application and want to discuss the compliance architecture requirements for your specific use case, get in touch with the Lycore team.


